

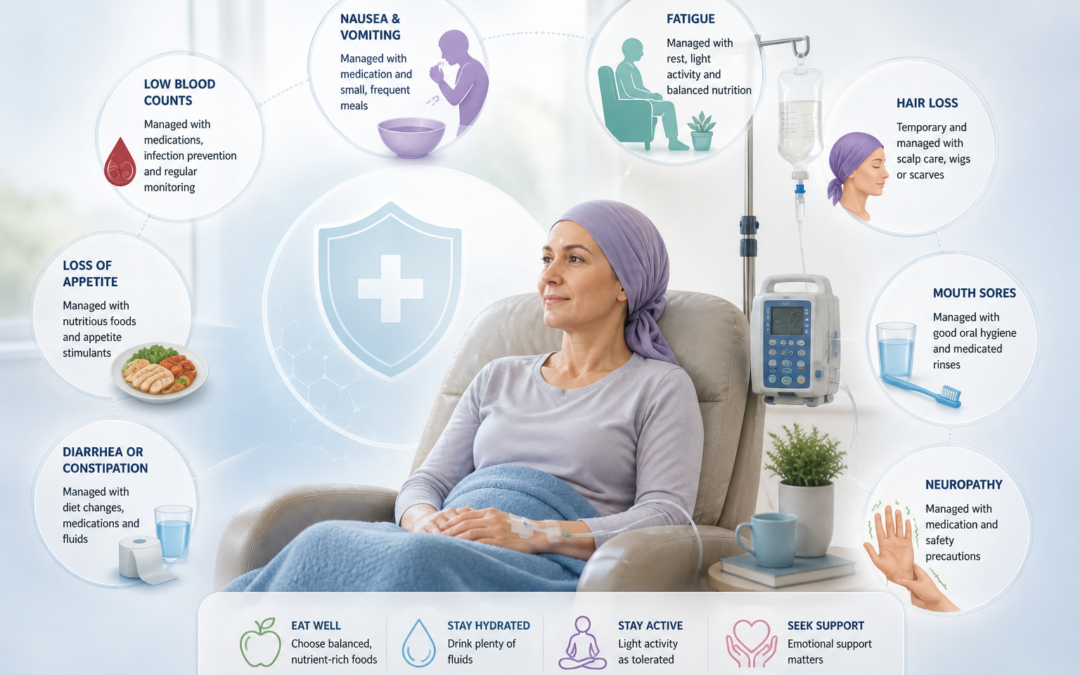
Chemotherapy drugs kill fast dividing cells. Cancer cells divide fast, and so do hair follicles, the lining of the gut and the bone marrow, and the drug cannot tell them apart. That is why nausea, fatigue, hair loss, low blood counts and mouth sores are so common, and also why most of them can be predicted and planned for. So which side effects can be handled at home, and which need a call to the team the same day?Ask anyone who has been through treatment what caught them off guard and it is rarely the side effect itself. It is the timing nobody explained. Nausea that peaks three days after the cycle rather than during it. Fatigue that does not lift after eight hours of sleep, with legs that feel like concrete. Those are the things people say they wish they had been told.
Dr. Sandeep Nayak, who provides the Best Cancer Treatment in Bangalore, puts it this way. “Most chemotherapy side effects are predictable enough that we can get ahead of them. Nausea does not have to arrive before we treat it, and anaemia does not have to become severe before we do something about it. The patients who do well are usually the ones who were told clearly what to expect, what to watch for, and what is worth a call to the team instead of being managed quietly at home.”
Worried about side-effects after Chemotherapy?
Which Side Effects Can Turn Serious If Left Unreported?
Some side effects are uncomfortable but routine. These six should not be waited out.
- Fever during the nadir window. A temperature above 38°C between day 7 and day 14 after a cycle should be treated as febrile neutropenia until proven otherwise. This is not wait and see territory, because neutropenic sepsis can worsen within hours, and the emergency department, not the morning clinic, is the right place to go.
- Nausea that stops fluids going down. One day of nausea that settles is expected. Two or three days of not keeping water down lead to dehydration, electrolyte problems and sometimes an admission that could have been avoided. If anti nausea medicines are not working by day two, the team needs to hear that day. Our post on managing nausea during chemotherapy covers what usually helps.
- Neuropathy that gets worse with each cycle. Mild tingling after oxaliplatin is common and usually reversible. Tingling that spreads further up the hands or feet, turns painful, or starts to affect grip or balance needs a dose change before it becomes permanent, and the window to act narrows with every cycle it goes unreported.
- Mouth sores that stop eating. Grade 1 mucositis is uncomfortable but manageable at home. Large ulcers, trouble swallowing or significant bleeding, which is grade 3 or 4, need assessment the same day. Patients who quietly live on water and yoghurt for a week without telling anyone often end up admitted for IV nutrition, with the next cycle delayed.
- New breathlessness or chest pain. Some regimens carry heart and lung risks, bleomycin in ABVD and anthracyclines in breast cancer protocols for example. New breathlessness or chest discomfort should not be put down to anxiety. It needs assessment the same day, and our post on why chemotherapy causes fatigue helps separate ordinary treatment fatigue from symptoms that need urgent review.
- Significant unintended weight loss. A few kilograms over a course of treatment is common. Losing 5 percent or more of body weight in a single cycle, or losing a little every week until the patient has stopped mentioning it because it feels normal, affects how well treatment is tolerated and how well the immune system works. It calls for dietitian input, not reassurance.
If a symptom is on this list, calling early is never an overreaction.
How Are the Common Side Effects Managed Day to Day?
Most of the work happens before symptoms appear, which is why the support plan starts with the first cycle.
- Nausea and vomiting. Anti nausea medicines are given before each cycle and continued on a schedule, not only once nausea starts. Preventing it works far better than chasing it.
- Fatigue and anaemia. Haemoglobin is checked regularly because fatigue from anaemia can be corrected, and gentle regular movement tends to help more than bed rest.
- Hair loss. Scalp cooling can reduce hair loss with some regimens, though not all of them, and hair usually grows back within three to six months of finishing treatment.
- Mouth sores. Careful mouth care, including a medicated mouthwash such as chlorhexidine where it is prescribed, helps prevent mucositis and settle it once it starts.
- Low white cell counts. For regimens that commonly cause neutropenia, growth factor injections (G-CSF) can lower the risk, and a fever during this period always means an urgent call.
- Appetite and weight. Dietitian input early on, with nutrition counselling built around what the patient can actually eat during treatment.
Dose changes are part of management too. If a side effect keeps getting worse, the regimen can be adjusted instead of the patient being expected to put up with it.
What Determines the Right Treatment Approach for Chemotherapy?
-
Side effect management is built around the specific regimen
FOLFOX for colorectal cancer carries cold sensitivity and neuropathy risk. ABVD for lymphoma carries pulmonary toxicity risk. AC-T for breast cancer carries significant nausea, hair loss, and fatigue. The support protocol follows what the drugs actually do, not a generic chemotherapy plan.Reporting between cycles is what keeps it on track
Which symptoms to report immediately: fever above 38°C, not keeping fluids down for 24 hours, chest pain versus which ones to mention at the next visit is information patients need before they leave the clinic after the first cycle, not when a problem has already developed.The comparison with other treatments
For patients on combined chemo-immunotherapy, the side effect profiles of each component are different and managed differently. The blog on immunotherapy vs chemotherapy side effects covers where those profiles overlap and where they don’t.
Key Takeaways
- Most chemotherapy side effects are manageable, and many can be prevented with the right plan in place from the first cycle.
- The ones that cause the most trouble are the ones that go unreported for too long.
- Fever above 38°C, fluids that will not stay down, chest pain and sudden neurological symptoms should never wait for the next appointment.
- For questions about your own treatment, reach the team at +91 8035740000 or through the contact page.
FAQs
Do all chemotherapy drugs cause the same side effects?
No. Which side effects appear depends on which drugs are used. Taxanes cause hair loss and neuropathy, platinum drugs cause nausea and neuropathy, and alkylating agents affect the bone marrow most. The regimen decides the side effect profile.
How long do side effects last after chemotherapy finishes?
Most acute side effects settle between cycles. Hair comes back within three to six months of finishing. Neuropathy can linger and is sometimes permanent if the dose was not adjusted early enough, and fatigue often carries on for months after treatment ends.
When does a side effect need an emergency call?
A fever above 38°C during the nadir window, fluids that will not stay down for more than 24 hours, chest pain, or any sudden new neurological symptom. These do not wait for the next scheduled visit.
Can I exercise during chemotherapy?
Gently, yes. Regular light movement consistently gives better fatigue outcomes than complete rest. What suits you depends on how you are feeling on a given day, and the oncology team can advise on what makes sense for your situation.
References
- National Cancer Institute (NCI): Chemotherapy Side Effects
- American Cancer Society (ACS): Managing Chemotherapy Side Effects
Disclaimer
This content is published for educational and informational purposes only and is not a substitute for medical advice. Please speak to your oncologist before changing or stopping any treatment.