

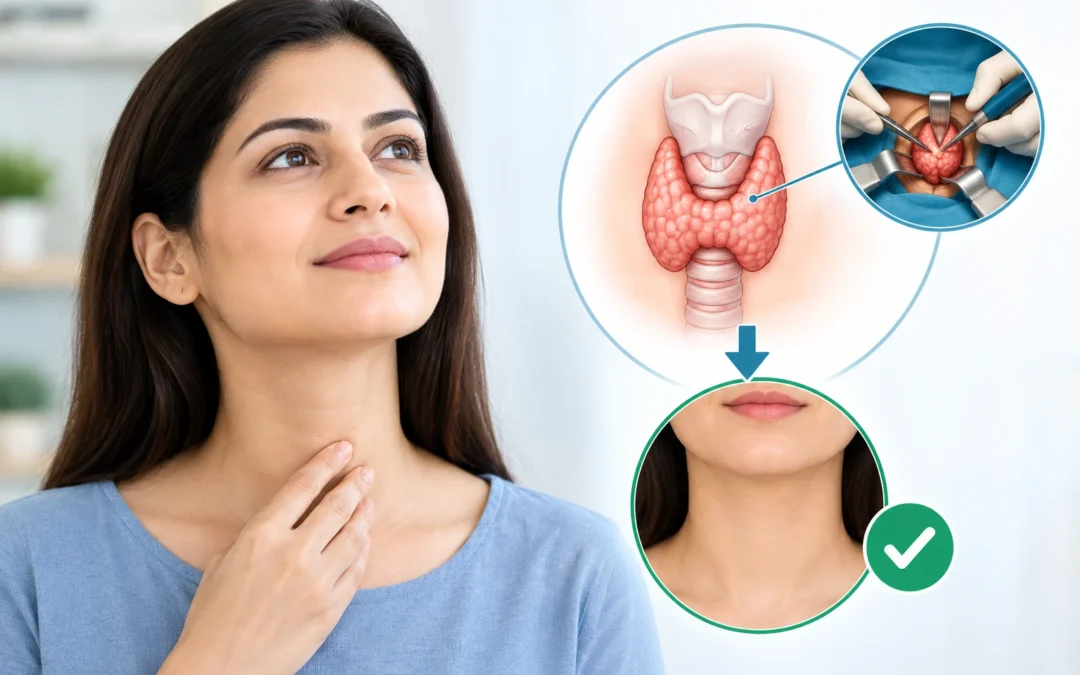
Yes, for some patients. The thyroid sits low in the front of the neck, so the usual operation goes through a cut there. Other routes reach the gland through the armpit, the chest, the mouth or behind the ear, so nothing shows on the front of the neck. These are specialised techniques, and they are not right for everyone. The scar also doesn’t vanish. It moves somewhere easier to hide.
Dr. Sandeep Nayak, who provides cancer treatment in Bangalore says the first question is usually about appearance, and the second should be about suitability. “Patients ask whether they can avoid a neck scar, and for the right person the answer is yes. But the operation has to be safe and complete first. Whether a hidden-scar approach is suitable depends on the size of the nodule, the type of disease and the patient’s anatomy, and it is decided case by case.”
Learn about scarless thyroid surgery approaches, their benefits and limitations, and whether they may be suitable for your condition.
How Is Thyroid Surgery Done Without a Neck Scar?
Thyroid surgery without a neck scar generally means reaching the gland from a distance, using a camera and fine instruments, sometimes with robotic assistance.
Through the armpit or chest. Small cuts in the armpit or near the breast let the surgeon tunnel up to the neck. The robotic axillo-breast approach, often called RABIT, works this way.
Through the mouth. In the transoral approach, small cuts are made inside the lower lip, so there is no scar on the skin.
Behind the ear. A cut hidden in the hairline behind the ear is used in some centres.
A tunnel under the skin. In every route the surgeon makes a working space under the skin, which is why these operations usually take longer than the standard one. Our blog on total vs partial thyroidectomy explains what is actually removed, which does not change with the route.
Who Is Suitable for a Scarless Approach?
What Determines the Right Treatment Approach?
The choice between a standard and a scarless operation comes down to several things the surgical team reviews together.
What the disease is. A benign nodule, a small low-risk cancer and an advanced cancer are handled differently.
How much of the thyroid needs to come out. Removing one side or the whole gland affects which route is practical.
Whether the lymph nodes are involved. Nodes in the neck usually need access that a hidden-scar route may not give safely.
Safety and completeness first. Cancer removal and protecting the voice nerve and parathyroid glands take priority over appearance.
The surgeon’s experience with the technique. These are skill-dependent operations, so ask how often your surgeon performs the particular approach.
Time, cost and your preference. The operation is often longer, and cost can differ. Our blog on the cost of robotic thyroid surgery in Bangalore covers this in more detail.
The final decision follows the scans, the biopsy result and a discussion of the options. More on thyroid care is on the thyroid cancer page.
Key Takeaways
-
Cancer is rarely down to genes alone. Age, lifestyle, where you live and plain bad luck all feed into it.
-
A brother or sister shares only about half your genes, so two siblings can carry quite different risk.
-
Inherited cancer is the smaller part of the story. But if the same cancer keeps turning up in a family, or turned up young, mention it to your doctor.
-
A genetic test can show whether you’ve inherited a risky gene change. If you have, screening can start earlier.
-
Has a sibling just been diagnosed? Use it as a reason to sit down with a doctor and go over your own family history and screening.
-
For questions about your own situation, you can contact the clinic at +91 9482202240.
FAQs
If my sibling has cancer, will I get it too?
Most likely not, and I’d want you to hear that first. Most people whose brother or sister has cancer never develop it. Where we pay closer attention is when several relatives have had the same cancer, or when someone was diagnosed young. That can point to a gene running in the family, and it’s worth checking.
Should I get genetic testing if my sibling had cancer?
Maybe. It depends on which cancer it was and what the rest of the family looks like. If your sibling was young when diagnosed, or it’s a type that tends to cluster (breast, ovarian or bowel), testing starts to make sense. A genetic counsellor can sort that out in one conversation. Often it’s best if the sibling who had cancer gets tested first, because that result tells you what to look for.
Can lifestyle changes lower my risk?
Yes, whatever your genes say. Don’t smoke, cut back on alcohol, keep moving and watch your weight. It won’t guarantee anything. But it does shift the odds, and it’s the one part of all this that’s entirely in your hands.
When should screening start if cancer runs in my family?
Often earlier than the standard age. A common rule of thumb is to begin about ten years before your relative’s age at diagnosis, so a sibling diagnosed with bowel cancer at 45 could mean starting at 35. It isn’t the same for every cancer, though, so let your doctor set the plan.
Reference
- American Thyroid Association — Thyroid Surgery Patient Information Read the Thyroid Surgery brochure
- National Cancer Institute — Thyroid Cancer Treatment (PDQ) Read the patient information guide
- Peer-reviewed review — Vestibular Approach for Thyroid Surgery: A Comprehensive Review (2024) Read on PubMed
Disclaimer:
This content is published for educational and informational purposes only and is not a substitute for medical advice. Please consult your doctor before changing any treatment.