

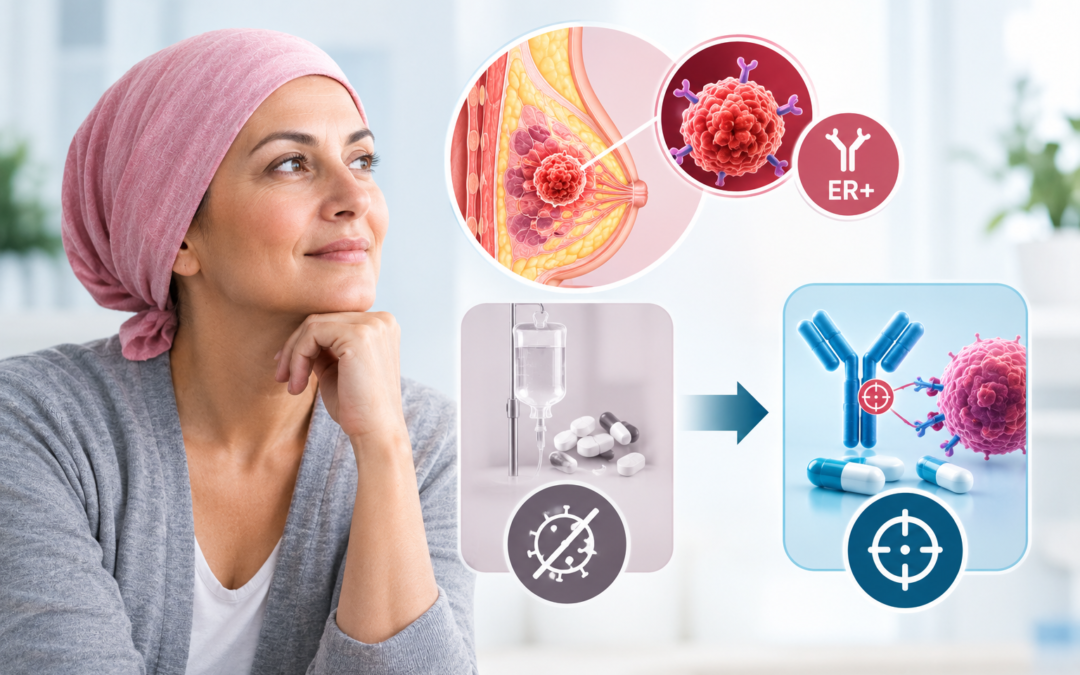
Yes, targeted therapy can often replace or delay chemotherapy in ER-positive breast cancer. For many patients with hormone receptor-positive, HER2-negative disease, hormone therapy paired with a CDK4/6 inhibitor like palbociclib, ribociclib or abemaciclib is now the standard first step. Whether chemo can be skipped altogether comes down to the stage, the tumor’s features and your general health.
Dr. Sandeep Nayak, who provides the best cancer treatment in Bangalore, says patients often hear “targeted therapy” and assume it means no chemo, ever. “Sometimes that’s true. In advanced ER-positive disease, targeted treatment is often where we start. In early breast cancer, we look at the genomic score, the lymph nodes and the stage first. Chemo isn’t the villain, and it isn’t always avoidable. It’s one tool, and we match it to the tumor.”
Already on treatment and worried about your heart?
Targeted Therapy vs. Chemotherapy: Which Is Right for ER+ Breast Cancer?
People always ask which one is “stronger”. That’s the wrong question, because they work in completely different ways:
- Targeted therapy goes after whatever is feeding this particular cancer. ER-positive cells run on estrogen. Hormone therapy cuts that supply, and a CDK4/6 inhibitor jams the switch that tells a cell to divide again. Chemo has no such aim. It hits anything that’s dividing fast, so your hair, your gut and your blood counts take the hit.
- If the cancer has already spread, this combination is usually where we start. Hormone therapy plus a CDK4/6 inhibitor is now standard for HR-positive, HER2-negative disease. For most patients it keeps the cancer in check for longer than chemo alone would, and day-to-day life is often easier while it works.
-
- In early-stage disease, a genomic test often decides it. For many women with a low score and few or no affected nodes, chemo adds little and can be skipped. Our precision oncology service handles that testing.
- “Gentler” doesn’t mean side-effect free. Targeted drugs can cause low white cell counts, tiredness and diarrhea, and some need heart rhythm and liver checks. So you’re monitored closely either way.
When Chemotherapy Is Still the Right Call?
Why Choose MACS Clinic for ER-Positive Breast Cancer Treatment?
Choosing between chemo and targeted therapy shouldn’t hinge on one doctor’s habit. At MACS Dr. Sandeep Nayak (MBBS, DNB Surgical Oncology, MRCS UK) is the founder and Chief of Surgical Oncology at MACS Clinic and Executive Director of Surgical Oncology and Robotic Surgery at KIMS Hospital. He introduced IORT using Intrabeam in India and performs minimally invasive and robotic cancer surgery. For ER-positive breast cancer, he works with medical oncologist Dr. Suresh Babu and radiation oncologist Dr. Nisha Vishnu to decide whether you need chemo, targeted therapy, or both. For a second opinion, the Expert Opinion consultation gives you a written plan.
Want a clear answer on whether chemo is really needed? Call +91 9482202240.
FAQs
Will I need chemo if my breast cancer is ER-positive?
Not always; early-stage cancers with low genomic risk may not need chemotherapy, while advanced cases often start with hormone therapy and targeted drugs.
Is targeted therapy weaker than chemo?
No, targeted therapy can control advanced ER-positive breast cancer longer than chemotherapy, though fast-growing cancers may need chemo first.
How many years will I be on a CDK4/6 inhibitor?
Treatment may last two to three years after surgery or continue for as long as it works and remains tolerable in advanced cancer.
What are the side effects of targeted therapy for ER-positive breast cancer?
Common side effects include fatigue, low blood counts, nausea, and diarrhea, with regular blood tests and other monitoring as needed.
Reference
- CDK4/6 Inhibitors vs Chemotherapy and Endocrine Therapy in HR-Positive, HER2-Negative Metastatic Breast Cancer, PubMed Central
- First-Line Chemotherapy Versus CDK4/6 Inhibitors in HR-Positive, HER2-Negative Breast Cancer With Liver Metastases, PubMed Central
- Dr. Yardley on the Utility of CDK4/6 Inhibitors in Metastatic HR+ Breast Cancer, OncLive
- Breast Cancer Treatment in Bangalore, MACS Clinic
Disclaimer:
This content is published for educational and informational purposes only and is not a substitute for medical advice. Please consult your doctor before changing any treatment.